1. Laryngectomy with radical neck dissection: removal of entire larynx, lymph nodes, submandibular salivary gland, sternomastoid muscle, spinal accessory nerves, and jugular vein for cancer of the larynx that extends beyond the vocal cords. Permanent tracheostomy; new methods of speech will have to be learned.

    Partial laryngectomy: removal of lesion on larynx. Patient will be able to speak after operation, but quality of voice may be altered.

    1. Assessment:
      1. Subjective data:
        1. Feeling of lump in throat.
        2. Pain: Adam’s apple; may radiate to ear.
        3. Dysphagia.
      2. Objective data:
        1. Hoarseness: persistent (longer than 2 weeks), progressive.
        2. Lymphadenopathy: cervical.
        3. Breath odor: foul.
    2. Analysis/nursing diagnosis:
      1. Impaired verbal communication related to removal of larynx.
      2. Body image disturbance related to radical neck dissection.
      3. Ineffective airway clearance related to copious amounts of mucus.
      4. Fear related to diagnosis of cancer.
      5. Impaired swallowing related to edema.
      6. Impaired social interaction related to altered speech.
    3. Nursing care pian/implementation:
      1. Preoperative care:
        1. Goal: provide emotional support and optimal physical preparation.
          1. Encourage verbalization of fears; answer all questions honestly, particularly about having no voice after surgery.
          2. Visit from person with laryngectomy (contact New Voice Club, Lost Chord, or International Association of Laryngectomees).
        2. Goal: health teaching.
          1. Prepare for tracheostomy.
          2. Other means to speak (esophageal “burp” speech, tracheoesophageal prosthesis or electronic artificial larynx).
      2. Postoperative care:
        1. Goal: maintain patent airway and prevent aspiration.
          1. Position: semi-Fowler’s (elevate 30-45 degrees), preventing forward flexion of neck to reduce edema and keep airway open.
          2. Observe for hypoxia:
            1. Early signs: increased respiratory and pulse rates, apprehension, restlessness.
            2. Late signs: dyspnea, cyanosis; swallowing difficulties-patient should chew food well and swallow with water.
          3. Laryngectomy tube care:
            1. Observe for stridor (coarse, high-pitched inspiratory sound)- report immediately.
            2. Have extra laryngectomy tube at bedside.
            3. Suction with sterile equipment; 2-3 mL of sterile saline into stoma may be used to loosen secretions.
        2. Goal: promote optimal physical and psychological function.
          1. Frequent mouth care.
          2. Wound: exposed site; note color and amount of drainage.
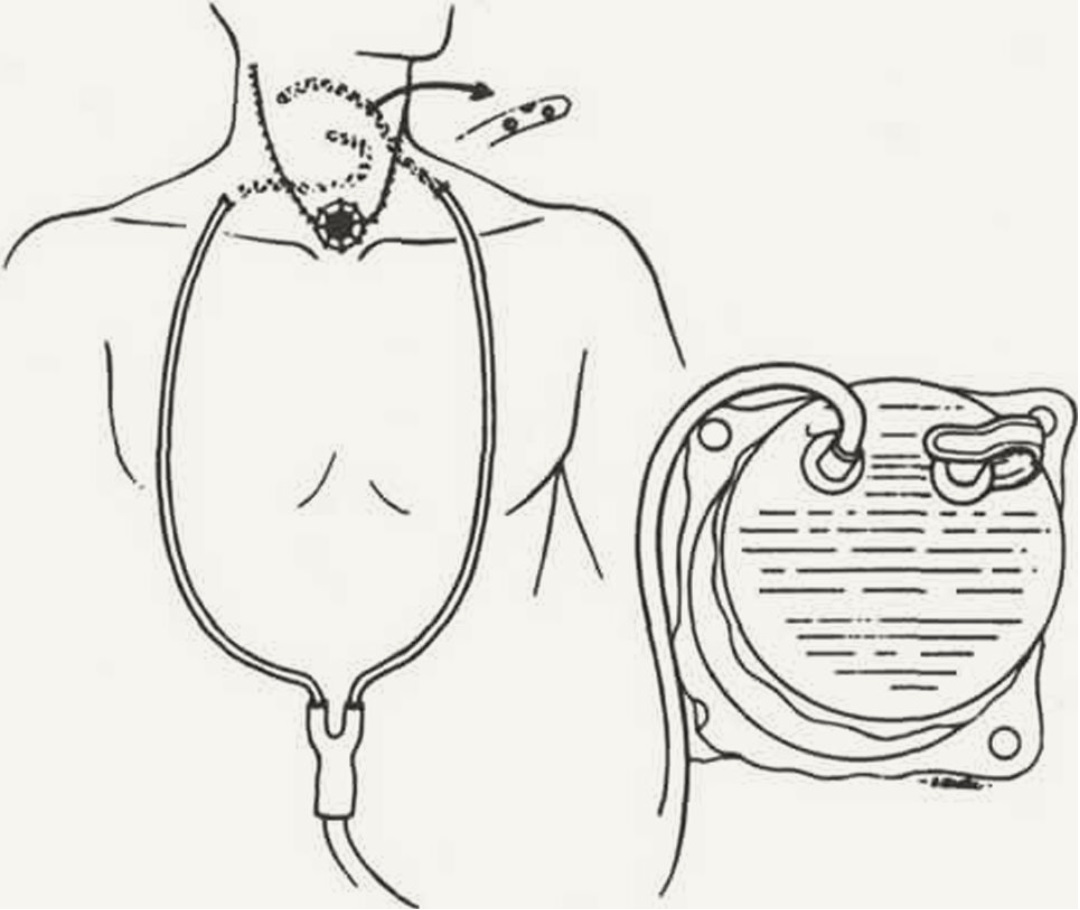
          3. Tubes: closed drainage system (Hemovac, fackson-Pratt); expect <100 up to 300 mL of serosanguineous drainage first postoperative day; drainage should decrease daily; observe patency.
          4. Post-drainage system removal-observe: skin flaps down, adherent to underlying tissue.
          5. Use surgical asepsis.
          6. Answer call bell immediately; use preestablished means of communication.
          7. Reexplain all procedures while giving care.
          8. Support head when lifting.
        3. Goal: health teaching.
          1. Speech rehabilitation as soon as esophageal suture is healed.
            1. Information on laryngeal speech (International Association of Laryngectomees, American Cancer Society, American Speech and Hearing Association).
            2. Esophageal speech best learned in speech clinic-learn to burp column of air needed for speech; new voice sounds are natural but hoarse.
          2. Stoma care:
            1. Cover with scarf or shirt made of a porous material (material substitutes for nasal passage-warms and filters out particles).
            2. Use source of humidification (“mister” or commercial humidifier).
            3. Caution while bathing or showering, to decrease likelihood of aspiration.
            4. Swimming not recommended.
            5. Procedure for suctioning if cough ineffective.
          3. Simple ROM of neck; how to support head.
          4. Possible contraindications: use of talcum powder, tissues.
    4. Evaluation/outcome criteria:
      1. No surgical complications (airway obstruction, infection, hemorrhage).
      2. Learns alternative speech 30-60 days after surgery.
      3. Demonstrates proper stoma care.
      4. Resumes productive lifestyle (work, family).
      5. Normal response to change in body image (anger, grief, denial).

Closed drainage system for constant suction. Suction is maintained by a plastic container. The container serves as both suction source and receptacle for blooIt is emptied as required, and drainage tubes are left in the neck for approximately 3 days.


  1. Aphasia: impaired ability to understand or use commonly accepted words or symbols; interferes with ability to speak, write, or read; language center-usually left hemisphere (85% of population). Dysarthria is motor impairment-inability to articulate words.
    1. Types and pathophysiology:
      1. Receptive (sensory)-lesion usually Wernicke’s area of temporal lobe; difficulty understanding spoken word (auditory aphasia) or written word (visual aphasia).
      2. Expressive (motor)-difficulty expressing thoughts in speech or writing (motor aphasia); understands written and spoken words. Three types: anomic-fluent speech, but unable to name objects, qualities, and conditions; fluent-articulate and grammatically correct, but no content or meaning; nonfluent-unable to select, organize, and initiate speech (involves Brocas area of brain); may affect writing.
    2. Risk factors:
      1. Vascular disease of the brain (cerebrovascular accident).
      2. Alzheimer’s disease (degeneration).
      3. Tumor.
      4. Trauma.
    3. Analysis/nursing diagnosis:
      1. Impaired verbal communication related to cerebral cortex disorder.
      2. Powerlessness related to inability to express needs/concerns.
      3. Impaired social interaction related to difficulty communicating.
    4. Nursing care plan/implementation: Goal: assist with communication: patient does best when rested; small improvements will occur up to 1 year after injury (age is a factor). Strategies: Nonfluent -allow time to respond; support efforts to speak; acknowledge frustration of patient-anticipate needs when appropriate; use picture board or flashcards, pointing, to encourage communication; assess efforts to communicate with open-ended questions. Fluent-face the patient, speak slowly and distinctly, not loudly; use gestures, repeat instructions as needed; involve family in techniques to improve communication; acknowledge frustration.
    5. Evaluation/outcome criteria:
      1. Communication reestablished.
      2. Minimal frustration exhibited.
      3. Participates in speech therapy.

  2. Meniere’s disease: chronic, recurrent disorder of inner ear; attacks of vertigo, tinnitus, and vestibular dysfunction; lasts 30 minutes to full day; usually no pain or loss of consciousness.
    1. Pathophysiology: associated with excessive dilation of cochlear duct (unilateral) from overproduction or decreased absorption of endolymph (endolymphatic hydrops)-progressive sensorineural loss.
    2. Risk factors:
      1. Emotional or endocrine disturbance (diabetes mellitus).
      2. Spasms of internal auditory artery.
      3. Head trauma.
      4. Allergic reaction.
      5. High salt intake.
      6. Smoking.
      7. Ear infections.
    3. Assessment:
      1. Subjective data:
        1. Tinnitus (constant or intermittent).
        2. Headache; feeling of fullness or pressure in affected ear.
        3. True vertigo: sudden attacks; room appears to spin.
        4. Depression; irritability; withdrawal.
        5. Nausea with sudden head motion.
      2. Objective data:
        1. Impaired hearing, especially low tones.
        2. Change in gait; lack of coordination.
        3. Vomiting with sudden head motion.
        4. Nystagmus-during attacks.
        5. Diagnostic test: caloric (cold water in ear canal)-may precipitate attack; audiometry-loss of hearing.
    4. Analysis/nursing diagnosis:
      1. Risk for injury related to vertigo, lack of coordination.
      2. Auditory sensory/perceptual alteration related to progressive hearing loss.
      3. Anxiety related to uncertainty of treatment.
      4. Risk for activity intolerance related to sudden onset of vertigo.
      5. Sleep pattern disturbance related to tinnitus.
      6. Ineffective individual coping related to chronic disorder.
    5. Nursing care plan/implementation:
      1. Goal: provide safety and comfort during attacks.
        1. Activity: bed rest during attack; side rails up; lower to chair or floor if attack occurs while standing; assist with ambulation (sudden dizziness common).
        2. Position: recumbent; affected ear uppermost usually.
        3. Identify prodromal symptoms (aura, ear pressure, increased tinnitus).
      2. Goal: minimize occurrence of attacks.
        1. Give medications as ordered:
          1. Anticholinergics (oral or transdermal scopolamine, atropine, glycopyrrolate [Robinul]) to minimize GI symptoms.
          2. Antihistamines (dimenhydrinate [Dramamine], diphenhydramine HC1 [Benadryl]) to sedate vestibular system.
          3. Antiemetics and antivertigo agents (diazepam [Valium], meclizine HC1 [Antivert]).
          4. Diuretics may help (hydrochlorothiazide) to decrease endolymphatic fluid.
        2. Diet: low sodium (<2 g/day).
        3. Avoid precipitating stimuli: bright, glaring lights; noise; sudden jarring; turning head or eyes (stand in front of patient when talking).
      3. Goal: health teaching.
        1. No smoking (causes vasospasm) or alcoholic beverages (fluid retention, contraindicated with medications).
        2. Management of symptoms: play radio to mask tinnitus, particularly at night.
        3. Keep medication available at all times.
        4. Prepare for surgery if indicated (labyrinthectomy if hearing gone; or vestibular neurectomy to relieve vertigo and preserve hearing).
    6. Evaluation/outcome criteria:
      1. Decreased frequency of attacks.
      2. Complies with treatment regimen and restrictions (low-sodium diet, no smoking).
      3. Hearing preserved.
  1. Otosclerosis: disease of the bone of otic capsule; insidous, progressive deafness; most common cause of conductive deafness; cause unknown.
    1. Pathophysiology: formation of new spongy bone in labyrinth-fixation of stapes-prevention of sound transmission through ossicles to inner ear fluids.
    2. Risk factors:
      1. Heredity.
      2. Women, puberty to 45 years
      3. Pregnancy.
    3. Assessment:
      1. Subjective data:
        1. Difficulty hearing-gradual loss in both ears.
      2. Diagnostic tests:
        1. Rinne (tuning fork placed over mastoid bone)-reduced sound conduction by air and intensified by bone.
        2. Weber (tuning fork placed on top of head)-increased sound conduction to affected ear.
        3. Audiometry-diminished hearing ability.
    4. Analysis/nursing diagnosis:
      1. Auditory sensory/perceptual alteration related to hearing loss.
      2. Body image disturbance related to hearing aid.
      3. Ineffective individual coping related to grief reaction to loss.
      4. Impaired social interaction related to hearing loss.
    5. Nursing care plan/implementation, evaluation/ outcome criteria.

  2. Stapedectomy: removal of the stapes and replacing it with a prosthesis (steel wire, Teflon piston, or polyethylene); treatment for deafness due to otosclerosis, which fixes the stapes, preventing it from oscillating and transmitting vibrations to the fluids in the inner ear.
    1. Analysis/nursing diagnosis:
      1. Sensory/perceptual alteration related to edema and ear packing.
    2. Nursing care plan/implementation:
      1. Preoperative health teaching.
        1. Important to keep head in position ordered by physician postoperatively.
        2. Caution: sneezing, blowing nose (keep mouth open), vomiting, coughing-all of which increase pressure in eustachian tubes (blow one side gently).
        3. Breathing exercises.
      2. Postoperative:
        1. Goal: promote physical and psychological equilibrium.
          1. Position: as ordered by physician-varies according to preference.
          2. Activity: assist with ambulation; avoid rapid turning, which might increase vertigo.
          3. Dressings: check frequently; may change cotton pledget in outer ear.
          4. Give medications as ordered:
            1. Antiemetics.
            2. Analgesics.
            3. Antibiotics.
          5. Reassurance: reduction in hearing is normal; hearing may not immediately improve after surgery.
        2. Goal: health teaching.
          1. Ear care: keep covered outdoors; keep outer ear plug clean, dry, and changed.
          2. Avoid:
            1. Water in ear for 6 weeks:
              1. Use barrier when washing hair.
              2. Use two pieces of cotton; saturate outer piece with petroleum jelly.
            2. Pressure or vibration from loud noise, flying, or heavy lifting until advised by MD.
    3. Evaluation/outcome criteria:
      1. Hearing improves-evaluate 1 month postoperatively (may require hearing aid).
      2. Returns to work (usually 2 weeks after surgery).
      3. Continues medical supervision.
  1. Deafness: Hard of hearing-slight or moderate hearing loss that is serviceable for activities of daily living. Deaf-hearing is nonfunctional for activities of daily living.
    1. Risk factors:
      1. Conductive hearing losses (transmission deafness):
        1. Impacted cerumen (wax).
        2. Foreign body in external auditory canal.
        3. Defects (thickening, scarring) of eardrum.
        4. Otosclerosis of ossicles.
      2. Sensorineural hearing losses (perceptive or nerve deafness):
        1. Arteriosclerosis.
        2. Infectious diseases (mumps, measles, meningitis).
        3. Drug toxicities (quinine, streptomycin, neomycin SO4).
        4. Tumors.
        5. Head traumas.
        6. High-intensity noises.
      3. Central deafness:
        1. Tumors.
        2. Stroke (brain attack).
      4. Noise-induced or occupational noise hearing loss:
        1. Blast injury.
        2. Firearms.
        3. Loud music.
      5. Aging (presbycusis).
    2. Assessment-objective data:
      1. Inattentive or strained facial expression.
      2. Excessive loudness or softness of speech.
      3. Frequent need to clarify content of conversation or inappropriate responses.
      4. Tilting of head while listening.
      5. Lack of response when others speak.
    3. Analysis/nursing diagnosis:
      1. Auditory/sensory/perceptual alteration related to loss of hearing.
      2. Impaired social interaction related to deafness.
    4. Nursing care plan/implementation:
      1. Goal: maximize hearing ability and provide emotional support.
        1. Gain person’s attention before speaking; avoid startling.
        2. Provide adequate lighting so person can see you when you are speaking.
        3. Look at the person when speaking.
        4. Use nonverbal cues to enhance communication, e.g., writing, hand gestures, pointing.
        5. Speak slowly, distinctly; do not shout (excessive loudness distorts voice).
        6. If person does not understand, use different words; write it down.
        7. Use alternative communication system:
          1. Speech (lip) reading.
          2. Sign language.
          3. Hearing aid.
          4. Paper and pencil.
          5. Flash cards.
        8. Supportive, nonstressful environment; alert staff to patient’s hearing impairment.
      2. Goal: health teaching.
        1. Prepare for evaluative studies-audiogram.
        2. Appropriate community resources: National Association of Hearing and Speech Agencies for counseling services; National Association for the Deaf to assist with employment, education, legislation; Alexander Graham Bell Association for the Deaf, Inc., serves as information center for those working with the deaf; American Hearing Society provides educational information, employment services, social clubs.
        3. Use of hearing aid: care-(1) turn off aid when not using (open case at night to prevent draining battery); (2) keep extra battery available; (3) wash with mild soap and warm water; use pipe cleaner to remove wax; (4) do not wear aid in shower or with ear infection; (5) store same place every night and away from pets; (6) if aid does not work: check battery insertion, on-off switch, placement (if ear-molded aid), cleanliness.
        4. Safety precautions: when crossing street, driving.
    5. Evaluation/outcome criteria:
      1. Method of communication established.
      2. Achieves independence (use of Dogs for Deaf, special telephones, visual signals).
      3. Copes with lifestyle changes (minimal depression, anger, hostility).
  1. Glaucoma (acute and chronic): increased intraocular pressure; second most common cause of blindness.
    1. Pathophysiology:
      1. Acute (closed-angle)-impaired passage of aqueous humor into the circular canal of Schlemm due to closure of the angle between the cornea and the iris. Medical emergency; requires surgery.
      2. Chronic (open-angle)-degenerative changes in trabecular meshwork; local obstruction of aqueous humor between the anterior chamber and the canal. Most common; treated with medication (miotics, carbonic anhydrase inhibitors).
      3. Secondary-in some cases neovascularization (new vessels) may form; blocks passage of aqueous humor (uveitis, trauma, drugs, diabetes, retinal vein occlusion).
      4. Untreated: imbalance between rate of secretion of intraocular fluids and rate of absorption of aqueous humor-increased intraocular pressures-decreased peripheral vision-corneal edema-halos and blurring of vision-blindness.
    2. Risk factors-unknown, but associated with:
      1. Emotional disturbances.
      2. Hereditary factors.
      3. Allergies.
      4. Vasomotor disturbances.
    3. Assessment:
      1. Subjective data:
        1. Acute (closed-angle):
          1. Pain: severe, in and around eyes.
          2. Rainbow halos around lights.
          3. Blurring of vision.
          4. Nausea, vomiting.
        2. Chronic (open-angle):
          1. Eyes tire easily.
          2. Loss of peripheral vision.
          3. Dull, morning headache.
      2. Objective data:
        1. Corneal edema.
        2. Decreased peripheral vision.
        3. Increased cupping of optic disc.
        4. Tonometry-pressures >22 mm Hg.
        5. Pupils: dilated.
        6. Redness of eye.
    4. Analysis/nursing diagnosis:
      1. Visual sensory/perceptual alterations related to increased intraocular pressure.
      2. Pain related to sudden increase in intraocular pressure.
      3. Risk for injury related to blindness.
      4. Impaired physical mobility related to impaired vision.
    5. Nursing care plan/implementation:
      1. Goal: reduce intraocular pressure.
        1. Activity: bed rest.
        2. Position: semi-Fowler’s.
        3. Medications as ordered:
          1. Miotics (pilocarpine, carbachol); may not be effective with intraocular pressure (IOP) >40 mm Hg.
          2. Carbonic anhydrase inhibitors (acetazolamide [Diamox]).
          3. Anticholinesterase (demecarium bromide [Humorsol]) to facilitate outflow of aqueous humor.
          4. Ophthalmic beta blockers (timolol) to decrease IOP.
      2. Goal: provide emotional support.
        1. Place personal objects within field of vision.
        2. Assist with activities.
        3. Encourage verbalization of concerns, fears of blindness, loss of independence.
      3. Goal: health teaching.
        1. Prevent increased IOP by avoiding:
          1. Anger, excitement, worry.
          2. Constrictive clothing.
          3. Heavy lifting.
          4. Excessive fluid intake.
          5. Atropine or other mydriatics that cause dilation.
          6. Straining at stool.
          7. Eye strain.
        2. Relaxation techniques; stress management if indicated.
        3. Prepare for surgical intervention, if ordered: laser trabeculoplasty, trabeculectomy (filtering), laser peripheral iridotomy.
        4. Medications: purpose, dosage, frequency; eyedrop installation-(1) wash hands; (2) head back, expose conjunctiva of lower lid, instill in center without touching eyelashes or eye; (3) close eyes gently, apply slight pressure to corner of eye to decrease systemic absorption; (4) wait at least 2 minutes before instilling a second eyedrop medication; have extra bottle in case of breakage or loss.
        5. Activity: moderate exercise-walking.
        6. Safety measures: eye protection (shield or glasses); Medic Alert band or tag; avoid driving 1-2 hours after instilling miotics.
        7. Community resources as necessary.
    6. Evaluation/outcome criteria:
      1. Eyesight preserved if possible
      2. Intraocular pressure lowered (<22 mm Hg).
      3. Continues medical supervision for life-reports reappearance of symptoms immediately.
  1. Cataract: developmental or degenerative opacification of the crystalline lens.
    1. Risk factors:
      1. Aging (most common).
      2. Trauma (x-rays, infrared or possibly ultraviolet exposure).
      3. Systemic disease (diabetes).
      4. Congenital defect.
      5. Drug effects (corticosteroids).
    2. Assessment:
      1. Subjective data-vision: blurring, loss of acuity (see best in low-lit conditions); distortion; diplopia; photophobia.
      2. Objective data:
        1. Blindness: unilateral or bilateral (particularly in congenital cataracts).
        2. Loss of red reflex; gray or cloudy white opacity of lens.
    3. Analysis/nursing diagnosis:
      1. Visual sensory/perceptual alterations related to opacity of lens.
      2. Risk for injury related to accidents.
      3. Social isolation related to impaired vision.

  2. Cataract removal: removal of opacified lens because of loss of vision; extracapsular cataract extraction followed by intraocular lens (IOL) insertion is procedure of choice.
    1. Nursing care plan/implementation:
      1. Preoperative:
        1. Goal: prepare for surgery (ambulatory center). Antibiotic drops or ointment, mydriatic eyedrops as ordered; note dilation of pupils; avoid glaring lights; usually done under local anesthetic with sedation.
        2. Goal: health teaching. Postoperative expectations: do not rub, touch, or squeeze eyes shut after surgery; eye patches will be on; assistance will be given for needs; overnight hospitalization not required unless complications occur; mild iritis usually occurs.
      2. Postoperative:
        1. Goal: reduce stress on the sutures and prevent hemorrhage.
          1. Activity: ambulate as ordered, usually soon after surgery; generally discharged few hours after surgery.
          2. Position: flat or low Fowler's; on hack or turn to nonoperative side 3-4 weeks, because turning to operative side increases pressure.
          3. Avoid activities that increase IOP: straining at stool, vomiting, coughing, brushing teeth, brushing hair, shaving, lifting objects over 20 lb, bending, or stooping; wear glasses or shaded lens during day, eyeshield at night.
          4. Provide mouthwash, hair care, personal items within easy reach, “stepin” slippers to avoid bending over.
        2. Goal: promote psychological well-being with elderly, frequent contacts to prevent sensory deprivation.
        3. Goal: health teaching.
          1. If intraocular lens not inserted, prescriptive glasses may be used (cataract glasses); explain about magnification, perceptual distortion, blind areas in peripheral vision; guide through activities with glasses; need to look through central portion of lens and turn head to side when looking to the side to decrease distortion.
          2. Eye care: instillation of eyedrops (mydriatics and carbonic anhydrase inhibitors) to prevent glaucoma and adhesions if IOL not inserted; with IOL, steroid-antibiotic use
          3. Signs/symptoms of infection (redness, pain, edema, drainage); iris prolapse (bulging or pear-shaped pupil); hemorrhage (sharp eye pain, halfmoon of blood).
          4. Avoid: heavy lifting; potential eye trauma.
    2. Evaluation/outcome criteria:
      1. Vision restored.
      2. No complications (severe eye pain, hemorrhage).
      3. Performs self-care activities (instills eyedrops).
      4. Returns for follow-up ophthalmology care-recognizes symptoms requiring immediate attention.
  1. Retinal detachment: separation of neural retina from underlying retinal pigment epithelium.
    1. Risk factors:
      1. Trauma.
      2. Degeneration.
    2. Assessment:
      1. Subjective data:
        1. Flashes of light before eyes.
        2. Vision: blurred, sooty (sudden onset); sensation of floating particles; blank areas of vision.
      2. Objective data-ophthalmic exam: retina is grayish in area of tear; bright red, horseshoe shaped tear; B-scan ultrasonography.
    3. Analysis/nursing diagnosis:
      1. Visual sensory/perceptual alteration related to blurred vision.
      2. Anxiety related to potential loss of vision.
      3. Risk for injury related to blindness.
    4. Nursing care plan/implementation:
      1. Preoperative:
        1. Goal: reduce anxiety and prevent further detachment.
          1. Encourage verbalization of feelings; answer all questions; reinforce physician’s explanation of surgical procedures.
          2. Activity: bed rest; eyes usually covered to promote rest and maintain normal position of retina; side rails up.
          3. Position: according to location of retinal tear; involved area of eye should be in a dependent position.
          4. Give medications as ordered: cycloplegic or mydriatics to dilate pupils widely and decrease intraocular movement.
          5. Relaxing diversion: conversation, music.
        2. Goal: health teaching. Prepare for surgical intervention (often combination used):
          1. Cryopexy or cryotherapy-supercooled probe is applied to the sclera, causing a scar, which pulls the choroid and retina together.
          2. Laser photocoagulation-a beam of intense light from a carbon arc is directed through the dilated pupil onto the retina; seals hole if retina not detached.
          3. Scleral buckling-the sclera is resected or shortened to enhance the contact between the choroid and retina; frequently combined with cryopexy.
          4. Banding or encirclement-silicone band or strap is placed under the extraocular muscles around the globe.
          5. Pneumatic retinopexy-instillation of expandable gas or oil to tamponade tear.
      2. Postoperative:
        1. Goal: reduce intraocular stress and prevent hemorrhage.
          1. Position: flat or low Fowler’s; sandbags may be used to position head; turn to nonoperative side if allowed, retinal tear dependent; special positions may be prone, side-lying, or sitting with face down on table if gas or oil bubble injected; position may be restricted 4-8 days.
          2. Activity: bed rest; decrease intraocular pressure by not stooping or bending and avoiding prone position.
          3. Give medications as ordered:
            1. Cycloplegics (atropine).
            2. Antibiotics.
            3. Corticosteroids to reduce eye movements and inflammation and prevent infection.
          4. ROM-isometric, passive; elastic stockings to avoid thrombus related to immobility.
        2. Goal: support coping mechanisms.
          1. Plan all care with patient.
          2. Encourage verbalization of feelings, fears.
          3. Encourage family interaction.
          4. Diversional activities.
        3. Goal: health teaching.
          1. Eye care: eye patch or shield at night for about 2 weeks to prevent touching eye while asleep; dark glasses; avoid rubbing, squeezing eyes.
          2. Limitations: no reading, needlework for 3 weeks, no physical exertion for 6 weeks; OK to watch TV, walk, except with bubble restrictions.
          3. Medications: dosage, frequency, purpose, side effects: avoid nonprescription medications.
          4. Signs of redetachment: flashes of light, increase in “floaters,” blurred vision, acute eye pain.
    5. Evaluation/outcome criteria:
      1. Vision restored.
      2. No further detachment-recognizes signs and symptoms.
      3. No injury occurs-accepts limitations.

  2. Blindness: legally defined as vision less than 20/200 with the use of corrective lenses, or a visual field of no greater than 20 degrees; greatest incidence after 65 years.
    1. Risk factors:
      1. Glaucoma.
      2. Cataracts.
      3. Macular degeneration.
      4. Diabetic retinopathy.
      5. Atherosclerosis.
      6. Trauma.
    2. Analysis/nursing diagnosis:
      1. Visual sensory/perceptual alteration related to blindness.
      2. Impaired social interaction related to loss of sight.
      3. Risk for injury related to visual impairment.
      4. Self-care deficit related to visual loss.
    3. Nursing care plan/implementation:
      1. Goal: promote independence and provide emotional support.
        1. Familiarize with surroundings; encourage use of touch.
        2. Establish communication lines; answer questions.
        3. Deal with feelings of loss, overprotectiveness by family members.
        4. Provide diversional activities: radio, CDs, talking books, tapes.
        5. Encourage self-care activities; allow voicing of frustrations when activity is not done to satisfaction (spilling or misplacing something), to decrease anger and discouragement.
      2. Goal: facilitate activities of daily living.
        1. Eating:
          1. Establish routine placement for tableware, plate, glass.
          2. Help person mentally visualize the plate as a clock or compass (“3 o’clock” or “east”).
          3. Take person’s hand and guide the fingertips to establish spatial relationship.
        2. Walking:
          1. Have person hold your forearm: walk a half step in front.
          2. Tell the person when approaching stairs, curb, incline.
        3. Talking:
          1. Speak when approaching person; tell them before you touch them.
          2. Tell them who you are and what you will be doing.
          3. Do not avoid words such as “see” or discussing the appearance of things.
      3. Goal: health teaching.
        1. Accident prevention in the home.
        2. Community resources:
          1. Voluntary agencies:
            1. American Foundation for the Blind-provides catalogs of devices for visually handicapped.
            2. National Society for the Prevention of Blindness-comprehensive educational programs and research.
            3. Recording for the Blind, Inc.-provides recorded educational books on free loan.
            4. Lion’s Club.
            5. Catholic charities.
            6. Salvation Army.
          2. Government agencies:
            1. Social and Rehabilitation Service-counseling and placement services.
            2. Veterans Administration-screening and pensions.
            3. State Welfare Department, Division for the Blind-vocational.
    4. Evaluation/outcome criteria:
      1. Acceptance of disability-participates in selfcare activities, remains socially involved.
      2. Regains independence with rehabilitation.