|
DiseaseMeasles (Rubeola)
Agent: Virus
Source: Respiratory tract secretions, blood, and urine of infected person
Transmission: Usually by direct contact with droplets of infected person
Incubation period: 10 to 20 days
Period of communicability: From 4 days before to 5 days after rash appears but mainly during prodromal (catarrhal) stage
Mumps
Agent: Paramyxovirus
Source: Saliva of infected persons
Transmission: Direct contact with or droplet spread from an infected person
Incubation period: 14-21 days
Period of communicability: Most communicable immediately before and after swelling begins
|
| Clinical Manifestations | Therapeutic Management Complications/ | Nursing Considerations |
|---|---|---|
|
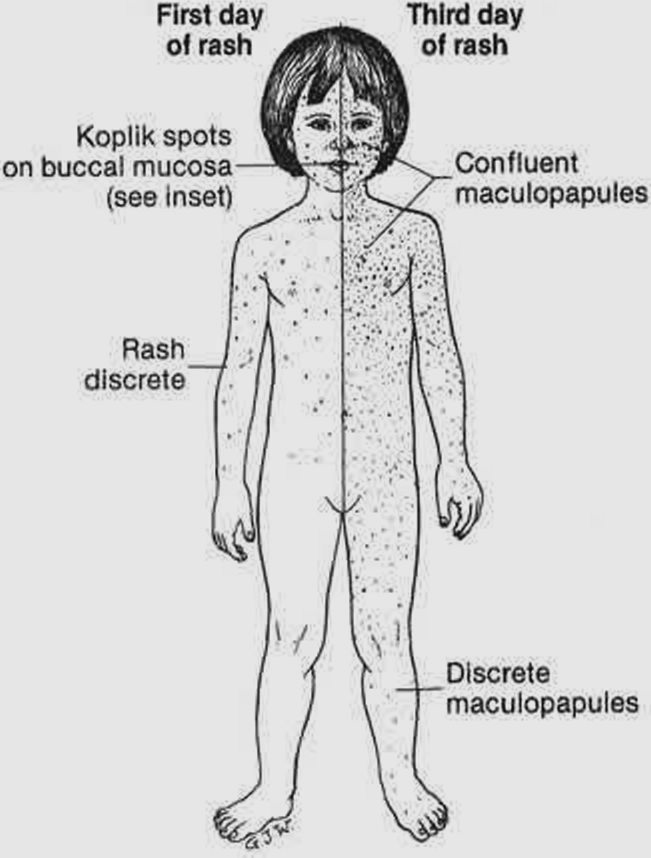
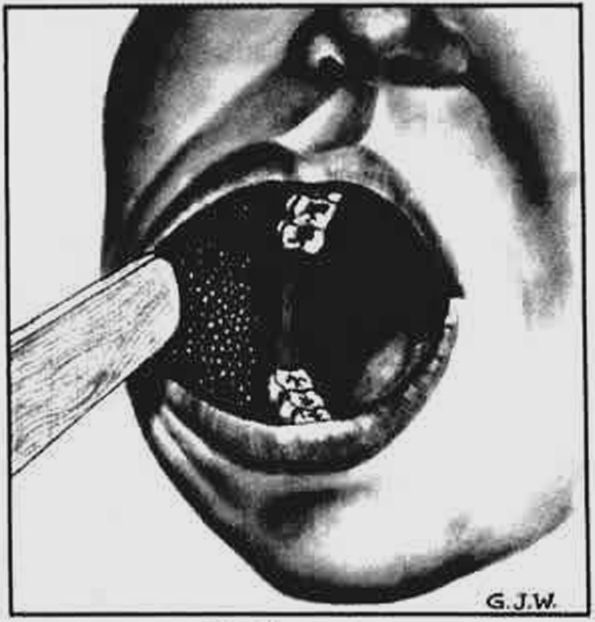
Prodromal (catarrhal) stage: Fever and malaise, followed in 24 hours by coryza, cough, conjunctivitis, Koplik spots (small, irregular red spots with a minute, bluish white center first seen on buccal mucosa opposite molars 2 days before rash); symptoms gradually increase in severity until second day after rash appears, when they begin to subside
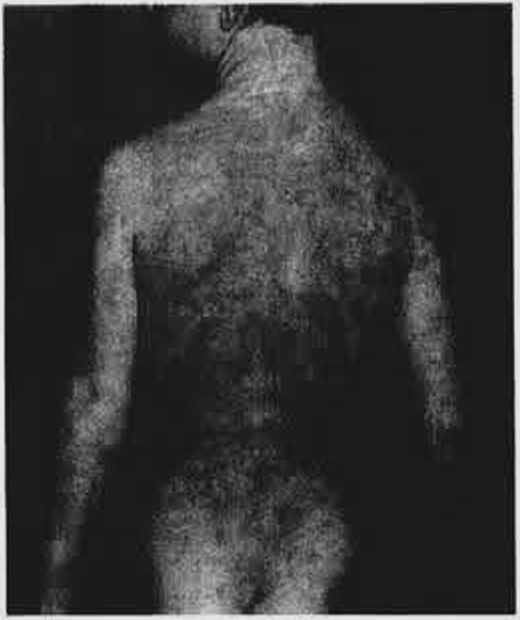
Rash: Appears 3-4 days after onset of prodromal stage; begins as erythematous maculopapular eruption on face and gradually spreads downward; more severe in earlier sites (appears confluent) and less intense in later sites (appears discrete); after 3-4 days assumes brownish appearance, and fine desquamation occurs over areas of extensive involvement
Constitutional signs and symptoms: Anorexia, malaise, generalized lymphadenopathy
|
Vitamin A supplementation
Supportive: Bed rest during febrile period
Antipyretics
Antibiotics to prevent secondary bacterial infection in high-risk children
Complications:
Otitis media
Pneumonia
Bronchiolitis
Obstructive laryngitis and laryngotracheitis
Encephalitis
|
Isolation until fifth day of rash; if hospitalized, institute respiratory precautions
Maintain bed rest during prodromal stage; provide quiet activity
Fever: Instruct parents to administer antipyretics; avoid chilling; if child is prone to seizures, institute appropriate precautions (fever spikes to 104°F (40°C) between fourth and fifth days)
Eye care: Dim lights if photophobia present; clean eyelids with warm saline solution to remove secretions or crusts; keep child from rubbing eyes; examine cornea for signs of ulceration
Coryza/cough: Use cool mist vaporizer; protect skin around nares with layer of petrolatum; encourage fluids and soft, bland foods
Skin care: Keep skin clean; use tepid baths as necessary
|
|
Prodromal stage: Fever, headache, malaise, and anorexia for 24 hours, followed by 'earache” that is aggravated by chewing
Parotitis: By third day, parotid gland(s) (either unilateral or bilateral) enlarge(s) and reach(es) maximum size in 1-3 days; accompanied by pain and tenderness
Other manifestations: Submaxillary and sublingual infection, orchitis, and meningoencephalitis
|
Symptomatic and supportive: Analgesics forpain and antipyretics for feverIntravenous fluid may be necessary for child who refuses to drink or vomits because of meningoencephalitis
Complications:
Sensorineural deafness
Postinfcctious encephalitis
Myocarditis
Arthritis
Hepatitis
Epididymo-orchitis
Sterility (extremely rare in adult males)
|
Isolation during period of communicability; institute respiratory precautions during hospitalization
Maintain bed rest during prodromal phase until swelling subsides
Give analgesics for pain; if child is unwilling to chew medication, use elixir form
Encourage fluids and soft, bland foods; avoid foods that require chewing
Apply hot or cold compresses to neck, whichever is more comfortingTo relieve orchitis, provide warmth and local support with tight-fitting underpants (stretch bathing suit works well)
|
| Disease | |
|---|---|
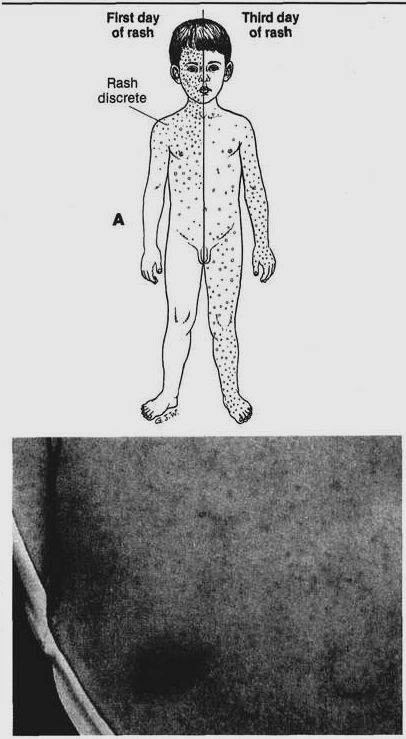
Rubella (German Measles). A, Progression of rash. B, Appearance of rash.
|
Rubella (German Measles)
Agent: Rubella virus Transmission: Direct contact and spread via infected person; indirectly via articles freshly contaminated with nasopharyngeal secretions, feces, or urine Incubation period: 14-21 days Period of communicability: 7 days before to approximately 5 days after appearance of rash Scarlet Fever Agent: Group A β-haemolytic streptococcal Source: Usually from nasopharyngeal secretions of infected person and carriers Transmission: Direct contact with infected person or droplet spread indirectly by contact with contaminated articles, ingestion of contaminated milk or other food Incubation period: 2-4 days, with range of 1-7 days Period of communicability: During incubation period and clinical illness approximately 10 days; during first 2 weeks of carrier phase although may persist for months
Scarlet fever. |
| Clinical Manifestations | Therapeutic Management Complications/ | Nursing Considerations |
|---|---|---|
|
Prodromal stage: Absent in children, present in adults and adolescents; consists of lowgrade fever, headache, malaise, anorexia, mild conjunctivitis, coryza, sore throat, cough, and lymphadenopathy; lasts for 1-5 days, subsides 1 day after appearance of rash
Rash: First appears on face and rapidly spreads downward to neck, arms, trunk, and legs; by end of first day, body is covered with a discrete, pinkish red maculopapular exanthema; disappears in same order as it began and is usually gone by third day
Constitutional signs and symptoms: Occasionally low-grade fever, headache, malaise, and lymphadenopathy
|
No treatment necessary other than antipyretics for low-grade fever and analgesics for discomfort
Complications:Rare (arthritis, encephalitis, or purpura); most benign of all childhood communicable diseases; greatest danger is teratogenic effect on fetus
|
Reassure parents of benign nature of illness in affected child
Use comfort measures as necessary
Isolate child from pregnant women
|
|
Prodromal stage: Abrupt high fever, pulse increased out of proportion to fever, vomiting, headache, chills, malaise, abdominal pain
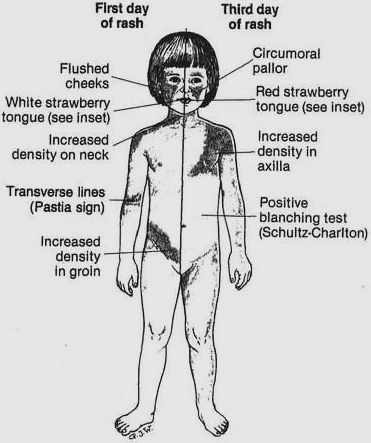
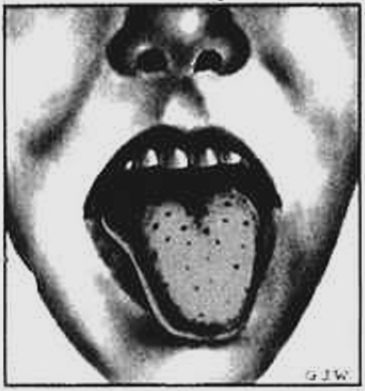
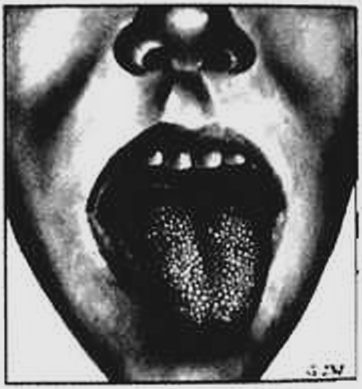
Enanthema: Tonsils enlarged, edematous, reddened, and covered with patches of exudate; in severe cases appearance resembles membrane seen in diphtheria; pharynx is edematous and beefy red; during first 1-2 days tongue is coated and papillae become red and swollen (white strawberry tongue); by fourth or fifth day white coat sloughs off, leaving prominent papillae (red strawberry tongue); palate is covered with erythematous punctate lesions
Exanthema: Rash appears within 12 hours after prodromal stage; red pinhead-sized punctate lesions rapidly become generalized but are absent on face, which becomes flushed with striking circumoral pallor; rash is more intense in folds of joints; by end of first week desquamation begins (fine, sandpaper-like on torso; sheetlike sloughing on palms and soles), which may be complete by 3 weeks or longer
|
Treatment of choice is a full course of penicillin (or erythromycin in penicillin-sensitive children); fever should subside 24 hr after beginning therapy
Antibiotic therapy for newly diagnosed carriers (nose or throat cultures positive for streptococci)
Supportive measures: Bed rest during febrile phase, analgesics for sore throat
Complications:
Otitis media
Peritonsillar abscess Sinusitis
Glomerulonephritis
Carditis, polyarthritis (uncommon)
|
Institute respiratory precautions until 24 hr after initiation of treatment
Ensure compliance with oral antibiotic therapy (intramuscular benzathine penicillin G [Bicillin] may be given if parents’ reliability in giving oral drugs is questionable)
Maintain bed rest during febrile phase; provide quiet activity during convalescent period
Relieve discomfort of sore throat with analgesics, gargles, lozenges, antiseptic throat sprays (Chloraseptic), and inhalation of cool mist
Encourage fluids during febrile phase; avoid irritating liquids (citrus juices) or rough foods; when child is able to eat, begin with soft diet
Advise parents to consult practitioner if fever persists after beginning therapy
Discuss procedures for preventing spread of infection
|